Emergency Dentist Treatment for Fractured Teeth and Roots

A fractured tooth can turn an ordinary day into a genuine emergency in seconds. One bite on a hard olive pit, an elbow during a weekend game, a fall on a wet kitchen floor, and suddenly there is sharp pain, bleeding, or the unnerving feeling that part of a tooth is moving when it should not. Root fractures are even more unsettling because the damage is often partly hidden. The crown may look only slightly chipped while deep inside the tooth and surrounding bone, the injury is much more serious.
This is where an Emergency Dentist becomes essential, not simply convenient. Fractured teeth and fractured roots are not problems to watch for a week and hope they settle down. Timing affects pain control, the odds of saving the tooth, the risk of infection, and the complexity of treatment. In practice, the first few hours matter more than most people realize.
The difficult part is that not all fractures behave the same way. A cracked cusp on a back molar is different from a front tooth snapped across the middle. A root fracture near the tip of the root is a very different situation from a vertical crack that runs down the length of the tooth. Some teeth can be bonded and monitored. Some need root canal treatment and stabilization. Some cannot be predictably saved, no matter how quickly the patient comes in. Good emergency care depends on sorting those categories accurately, fast, and with sound judgment.
What counts as a dental fracture emergency
Patients often assume a dental emergency means only severe pain or dramatic bleeding. In reality, many serious fractures present with surprisingly mild symptoms at first. A tooth may feel sore only when biting. It may click faintly. It may feel taller than the neighboring teeth. The gum may swell later, not immediately. Root fractures in particular can hide behind vague discomfort for days before the tooth starts to loosen or discolor.
An emergency evaluation is appropriate when a tooth breaks, cracks, shifts position after trauma, becomes loose, or causes sudden pain with chewing. It is also urgent when the fracture exposes yellow dentin or red pulp tissue, when a broken edge is cutting the tongue or cheek, or when swelling develops around the area. Even without dramatic pain, a tooth that has been hit hard enough to feel different deserves prompt examination.
In day to day dental practice, one of the more common mistakes is delay after sports injuries or falls. Adults often push through and assume they can wait until a routine appointment, especially if the tooth still looks mostly intact. Children may be even harder to assess because the pain response is inconsistent. Yet trauma can injure the nerve, the root, and the ligament around the tooth even when the visible damage appears minor. Early imaging, careful mobility testing, and follow up planning make a real difference.
The many ways a tooth can fracture
The word fractured sounds simple, but clinically it covers several very different injuries. A small enamel chip is the least serious version. It may need smoothing or bonding, mostly for comfort and appearance. A larger crown fracture involving dentin usually causes sensitivity to air, cold, and pressure. When the pulp is exposed, pain tends to be sharper and the risk to the vitality of the tooth increases.
Then there are cracks that do not break off a piece of tooth immediately. These can run through the crown and sometimes into the root. Patients often describe a brief, stabbing pain when releasing a bite, especially on hard foods. Molar teeth are common victims because they carry heavy chewing forces, and old large fillings can weaken the remaining tooth structure.
Root fractures occupy their own category. A horizontal root fracture cuts across the root, often after a blow to the mouth. A vertical root fracture runs lengthwise and is usually more difficult to save. Horizontal fractures can sometimes heal if the fragments are in a favorable position and the tooth is stabilized. Vertical root fractures usually have a much poorer prognosis because bacteria can track down the crack and inflame the bone around the root.
That distinction is not academic. It determines whether the goal is bonding, a crown, splinting, root canal treatment, surgical care, extraction, or close observation.
What an Emergency Dentist looks for first
The first emergency visit is not just about stopping pain. It is about answering a series of practical questions very quickly. Is the tooth restorable. Is the pulp exposed. Is the fracture above or below the gum line. Is the root involved. Has the tooth moved in the bone. Is the surrounding alveolar bone fractured as well. Are there missing fragments that could be reattached. Is there a risk of aspiration or soft tissue injury from broken pieces.
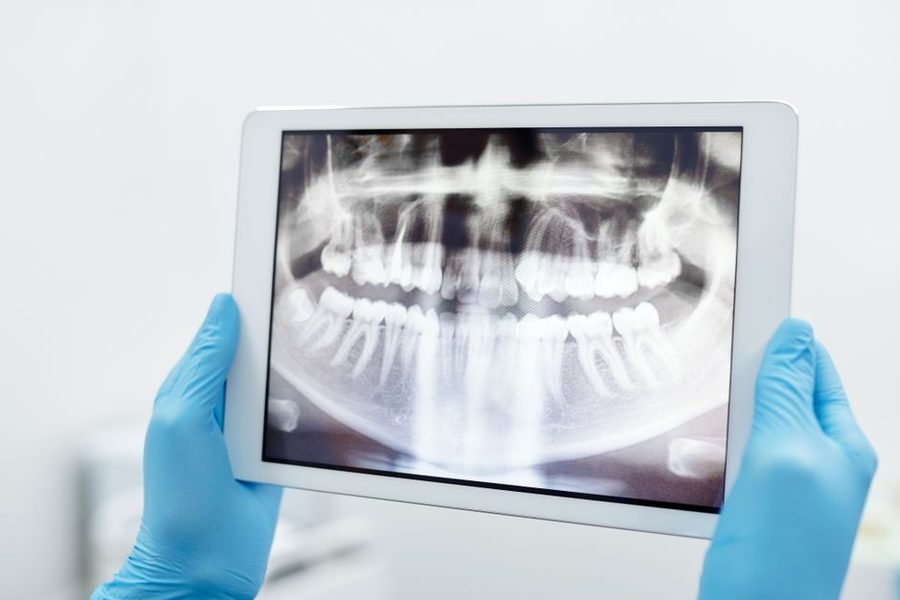
A thorough exam typically includes visual inspection, percussion testing, mobility testing, bite assessment, and radiographs. Standard dental x rays help, but they do not reveal every crack. Root fractures can be hard to catch if the angle of the image misses the fracture line. In some cases, additional views or three dimensional imaging are needed, especially when symptoms and plain films do not match.
Pulp testing may also be part of the exam, though trauma cases need interpretation with caution. A tooth may test non responsive right after an injury and recover later, or it may respond initially and lose vitality over time. That is why trauma care often involves both immediate treatment and structured follow up. A single emergency appointment rarely tells the full story.
There is also a practical human element. An experienced Emergency Dentist pays attention to how the injury happened. A front tooth broken during a bicycle fall raises one set of concerns. A molar that cracked while chewing on a seed raises another. Trauma history helps predict hidden damage.
The first few hours at home
Before a patient reaches the dental chair, the right first aid can reduce complications. Gentle handling matters. A cracked tooth can become a deeper fracture if someone keeps testing it with repeated biting. Mouth rinsing is useful, but vigorous swishing after trauma is not. If there is swelling, a cold compress on the outside of the face is usually more helpful than trying random home remedies.
If a piece of tooth has broken off, it is worth bringing it to the appointment. Sometimes a fragment can be bonded back, particularly with front teeth and clean fracture lines. If there is bleeding, pressure with clean gauze often helps. If the tooth is loose, it should not be pushed, twisted, or repeatedly checked.
The most useful short checklist is simple:
- Rinse gently with clean water to remove blood and debris.
- Save any broken fragment in a clean container.
- Use a cold compress outside the face for swelling.
- Avoid chewing on that side and do not test the tooth.
- Contact an Emergency Dentist as soon as possible.
This kind of restraint sounds obvious, but people often do the opposite. They chew carefully on the tooth to see if it is really broken, they brush aggressively over a bleeding gumline, or they postpone care because the pain fades once the initial shock passes. None of those choices improves the odds.
How crown fractures are usually treated
When the fracture is limited to enamel or enamel and dentin, the emergency goal is straightforward: protect the tooth, relieve pain, and restore form. Small chips can often be smoothed or repaired with tooth colored composite. Larger fractures may need a bonded build up, and if enough structure is missing, a crown may be recommended later for strength.
Front teeth deserve special mention because treatment decisions involve both biomechanics and esthetics. If the fragment is available and in good condition, reattachment can be an excellent option. It preserves natural translucency and shape in a way that is hard to fully copy. The drawback is that reattached fragments are not indestructible. Patients need to understand that the bond can be strong and still not recreate the original tooth’s resistance to future trauma.
When dentin is exposed, sensitivity control becomes a priority. Air, cold drinks, and even breathing through the mouth can hurt. Sealing the exposed surface quickly reduces discomfort and protects the tooth from bacterial irritation. If the fracture is deep enough to involve or threaten the pulp, treatment may shift toward pulp capping, pulpotomy in selected younger teeth, or full root canal therapy depending on the age of the patient, the stage of root development, and the degree of contamination.
When the pulp is exposed
A visible red spot or fresh bleeding from the center of a broken tooth often means pulp exposure. This raises the stakes. The pulp is the living tissue inside the tooth, containing nerves and blood vessels. Once exposed, it is vulnerable to contamination and inflammation. That does not always mean the tooth automatically needs a root canal the same day, but it does mean the decision window narrows.
In younger patients with immature permanent teeth, preserving pulp vitality can be especially valuable because the root may still be developing. In adults, the treatment plan depends on the size of the exposure, the time since injury, the symptoms, and whether the tooth can be sealed predictably. Small, fresh exposures sometimes respond well to conservative vital pulp treatment. Larger or contaminated exposures are more likely to end up with root canal therapy.
Good emergency care here is part technical skill, part judgment. The temptation is either to overtreat everything or to promise conservative outcomes where the biology is not favorable. Neither helps the patient. Honest prognosis matters from the first visit.
Root fractures are more complicated than they look
A root fracture changes everything because the visible break in the crown may be only half the problem, or there may be no crown break at all. The tooth may feel loose, displaced, or sore to bite on. Bleeding from the gum sulcus around the tooth can be a clue, especially after trauma. Sometimes the tooth appears slightly longer than its neighbors because it has been displaced.
Horizontal root fractures can occur in the apical third, middle third, or cervical third of the root. Location matters. Fractures closer to the root tip generally have a better prognosis than those near the neck of the tooth. If the coronal fragment is minimally displaced and can be repositioned and splinted, healing is possible. The pulp in the coronal portion may survive, or it may later require root canal treatment. The apical fragment often remains vital and untouched.
Cervical root fractures, those near the gumline, are among the most difficult injuries to manage. There is less stable structure to work with, and the leverage forces on that area are high. Even if the tooth can be temporarily stabilized, long term retention is uncertain.
Vertical root fractures are a different category again. They often occur in heavily restored teeth, root treated teeth, or teeth under repeated stress. Symptoms can mimic gum disease or a vague bite problem. A narrow isolated periodontal pocket, recurrent swelling near one root, or a sinus tract may point toward the diagnosis. Unfortunately, vertical root fractures are usually not repairable in a predictable way. Extraction is often the realistic treatment, particularly for single rooted teeth. Multi rooted teeth sometimes allow removal of only the affected root or part of the tooth, but that depends on anatomy and overall restorability.
Splinting and stabilization
When a tooth has been displaced or a root fracture is present, splinting may be part of emergency treatment. This usually means attaching the injured tooth to neighboring teeth with a flexible stabilizing material for a defined period. The goal is support, not rigid immobilization. Teeth need a small degree of physiological movement for the periodontal ligament to heal well.
Duration depends on the injury pattern. Many subluxation or root fracture cases need several weeks, while more complex injuries may require longer. The splint itself is only one part of treatment. Patients also need instructions on soft diet, oral hygiene, and follow up because a poorly cleaned splinted area can quickly become inflamed.
One practical point from experience: some patients feel immediate relief once the tooth is stabilized, and they assume the problem is solved. It is not. Splinting buys time and creates better healing conditions. It does not erase the possibility of later pulp necrosis, root resorption, or failure of the fracture site to heal.
When a tooth cannot be saved
No patient likes hearing that a fractured tooth or root is non restorable, especially if the crown still looks mostly present. Yet there are cases where extraction is the most appropriate treatment, not a defeat. Deep vertical root fractures, crown root fractures extending far below the bone, and teeth split into separate segments often have poor long term prognosis. Repeated attempts to save such teeth can become expensive, painful, and ultimately unsuccessful.
That said, extraction decisions should not be rushed purely because the case looks difficult. There is a meaningful difference between low probability and no realistic chance. Some teeth can be preserved with coordinated care involving endodontics, periodontics, or restorative reconstruction. Others should be removed because the biological foundation is gone. The key is clear explanation of benefits, burdens, and likely outcomes.
Patients appreciate candor when it is specific. Saying, “We can try, but here is what success would require and here is why failure risk is high,” is far more useful than vague optimism.
Pain management and infection risk
Not every fractured tooth causes severe pain immediately, but most become progressively more uncomfortable if left untreated. Exposed dentin is sensitive. Inflamed pulp can shift from a sharp response to cold into spontaneous throbbing. Cracks that flex under pressure create a biting pain that makes normal eating difficult. Soft tissue lacerations from sharp edges add another layer of discomfort.
Analgesics help, but they do not address the cause. Antibiotics are even more misunderstood. A clean fracture without spreading infection does not automatically need antibiotics. Dentists prescribe them when there are signs of infection, significant soft tissue contamination, certain trauma patterns, or medical factors that justify coverage. Using antibiotics as a substitute for treatment is poor care and often delays the real fix.
Local measures are often more effective than patients expect. Sealing exposed dentin, adjusting the bite to reduce pressure, smoothing a sharp edge, or stabilizing a mobile tooth can reduce pain quickly, often within the same visit.
What follow up really looks like
Fractured teeth are not always solved in one appointment. Even after excellent emergency treatment, healing and long term outcomes need monitoring. A traumatized tooth can remain vital and stable for years, or it can slowly develop pulpal necrosis months later. Root resorption may appear on later radiographs. Discoloration can develop over time, especially in anterior teeth.
This is why follow up intervals matter. Depending on the injury, the dentist may recommend review at a few weeks, several months, and again later with repeat imaging and vitality checks. Patients sometimes interpret this as uncertainty. In reality, it is responsible care. Dental trauma has a timeline, and biology does not always declare its final answer on day one.
Several factors shape prognosis more than patients expect:
- How quickly the tooth was evaluated after injury.
- Whether the root fracture is horizontal or vertical.
- The location of the fracture relative to the gum and bone.
- The degree of displacement or mobility.
- The amount of remaining sound tooth structure.
Those details influence not only whether a tooth can be saved, but how durable that result is likely to be.
Children, teenagers, and sports injuries
Younger patients deserve special mention because their teeth are still developing and trauma is common. A child who fractures a front tooth at school or during sports often arrives frightened, bleeding, and more upset about appearance than pain. In many of these cases, a calm and efficient emergency response makes a lifelong difference, both clinically and emotionally.
Immature permanent teeth have a stronger capacity for healing in some respects, yet they also require careful handling to preserve future development. A pulp exposure in a child is not managed exactly the same way as the same injury in a middle aged adult. Repositioning and splinting decisions also need to account for growth and root formation.
Mouthguards remain one of the most practical preventive tools in contact sports, but they are underused, especially in casual recreational play where parents assume risk is low. A large share of sports related dental injuries happen outside organized competition, in driveways, parks, and schoolyards.
Restoring function, not just appearance
Patients often focus first on what they can see in the mirror, especially with front teeth. That is understandable. But the real success of fracture treatment is broader. The tooth needs to function comfortably, maintain healthy surrounding tissues, fit properly into the bite, and remain serviceable over time.
A beautifully bonded front tooth that is left in traumatic occlusion may fail early. A molar rebuilt after a crack may look routine on an https://www.google.com/maps?cid=17479708580987630325 x ray but still need cuspal coverage to prevent the remaining walls from splitting later. A root treated fractured tooth often needs a thoughtful definitive restoration, not just a temporary patch. Emergency care is the first chapter, not the whole story.
Good dentists talk through these next steps early. Patients do better when they understand what is temporary, what is definitive, and what warning signs should trigger a return visit sooner than planned.
The most important judgment call
The central challenge in fractured tooth and root emergencies is deciding what can be predictably preserved and what cannot. That sounds simple until you are looking at a tooth with a jagged break, an anxious patient in pain, incomplete imaging, and a clock ticking late in the day. Experience matters here. So does restraint.
An Emergency Dentist is not just there to smooth a sharp edge and send the patient home. The real value lies in rapid diagnosis, pain control, protection of vulnerable tooth structures, stabilization where indicated, and an honest plan for what comes next. Sometimes that means same day conservative repair. Sometimes it means endodontic referral, temporary splinting, or extraction with a discussion about replacement options. The right treatment is the one that respects both the biology of the injury and the practical needs of the patient.
Fractured teeth and roots are stressful, but they are not all hopeless. Many are manageable, and some heal better than patients expect when treated promptly and properly. The common thread is speed, accurate assessment, and careful follow through. If a tooth has broken, shifted, or become painful after trauma, waiting rarely improves the picture. Prompt care gives that tooth its best chance.
Smyle Dental Bakersfield
2016 E St, Bakersfield, CA 93301, United States
+16614939040
FAQ About Emergency Dentist
What counts as a dental emergency?
Severe tooth pain, facial swelling, uncontrolled bleeding, a knocked-out or displaced tooth, and significant dental trauma may need prompt assessment. Trouble breathing or rapidly increasing swelling requires urgent medical help.
What should I do if a permanent tooth is knocked out?
Handle the tooth by the crown rather than the root, keep it moist, and contact a dentist immediately. Fast treatment can improve the chance of saving the tooth.
Can an emergency dentist treat severe tooth pain the same day?
Same-day care may be available depending on the cause and schedule. The dentist will examine the area, may take digital X-rays, and recommend treatment based on the diagnosis.
Should I go to the emergency room for dental swelling?
Seek urgent medical care for trouble breathing, difficulty swallowing, rapidly spreading facial swelling, or other severe symptoms. A dentist can assess the underlying dental cause and provide appropriate follow-up care.